In everyday conversation, “living will” and “advance directive” mean the same thing across Australia. Legally, though, the name your state uses, the form it takes, and how much weight it carries in a crisis can differ sharply, especially in New South Wales, which has no dedicated legislation. If you’re planning one, check your state’s official form or speak with your GP or a lawyer before you sign anything.
TL;DR:
- The enforceability of advance care directives varies significantly between states, with New South Wales relying on common law recognition rather than a dedicated act.
- Vague wording and improper signing are the most common reasons directives are challenged or ignored during emergencies or disputes.
- In NSW, a well-drafted, witnessed written directive with clinician confirmation about capacity provides the best legal protection.
- A substitute decision-maker must understand and faithfully follow your written wishes, especially under high-pressure situations.
- It is essential to review, update, and store your directive properly, ensuring all copies are accessible and current across your healthcare network.
Table of Contents
- What’s the difference between a living will and an advance care directive?
- Does every state have the same advance care directive laws?
- When does an advance care directive actually apply?
- How do you make a valid advance care directive?
- Who should you appoint as your substitute decision-maker?
- Where should you store your directive, and how do you update it?
- What legal problems most often derail an advance care directive?
- A lawyer’s view: when advance care directives need legal review
- Funding Your Legal Matter — No Win, No Fee
- Sources
- FAQ
What’s the difference between a living will and an advance care directive?
“Living will” is the term most Australians grew up hearing, usually from American television or films. It’s not a legal term used in any Australian statute. What the law actually refers to is an Advance Care Directive (ACD), and every state and territory uses its own name for the document:
- New South Wales: Advance Care Directive (recognised under common law, no dedicated Act)
- Victoria: Advance Care Directive
- Queensland: Advance Health Directive
- South Australia: Advance Care Directive
- Western Australia: Advance Health Directive
- Tasmania: Advance care planning documents (no dedicated statute)
- ACT: Health Direction
- Northern Territory: Advance Personal Plan
Beyond naming, there’s a more useful distinction: a values directive records your general wishes and priorities, while an instructional directive gives specific, binding instructions (“no resuscitation if I have suffered irreversible brain damage”). A valid Advance Care Directive should state values and, where you intend it, specific instructions clearly. The label on the form matters far less than whether the content is clear and was made voluntarily while you had capacity.
Does every state have the same advance care directive laws?
No. Statutory Advance Care Directives exist in every Australian state and territory except New South Wales, where directives are recognised under common law rather than a dedicated Act. That single fact changes how much certainty you get depending on where you live.
- States and territories with legislation (Victoria, Queensland, South Australia, Western Australia, ACT, Northern Territory): each has a prescribed or recommended form, witnessing requirements, and a clear statutory pathway for clinicians to follow.
- New South Wales: there’s no mandated form. A written, clearly expressed directive is still legally recognised, but its enforceability depends on how well it was drafted and witnessed, not on ticking a government form.
- Tasmania: similarly relies on common law and advance care planning guidance rather than a dedicated statute.
If you move interstate, don’t assume your existing directive travels with the same legal certainty. Check the destination state’s health department site for its accepted format, and if your original directive was made years ago under a different form, it’s worth having it reviewed against current guidance.
When does an advance care directive actually apply?
An ACD only switches on when you lack the capacity to make or communicate the specific medical decision in question. While you’re competent, your current wishes always override anything written earlier, even if it contradicts the document.
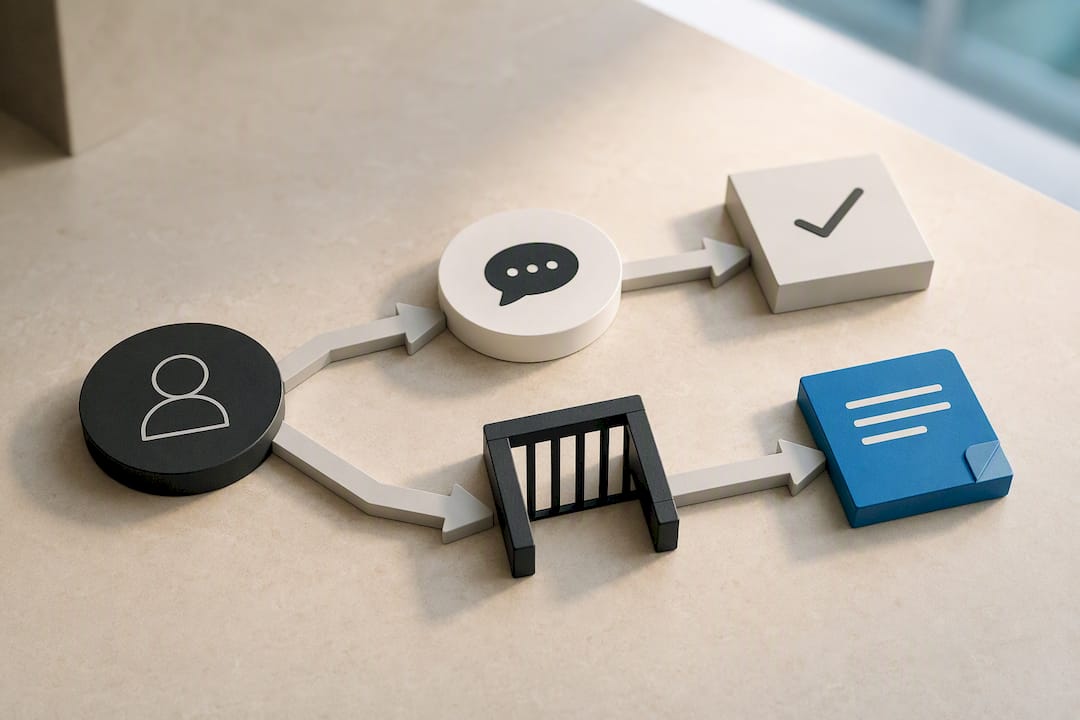
Picture someone who suffers a major stroke and is unconscious. Their ACD, if valid and located by clinicians, would guide treatment decisions from that point. Compare that to someone with early-stage dementia who can still clearly express what they want that day; their live decision takes priority over the directive.
An ACD is not a Will. It has no power over your assets after death, and it cannot authorise voluntary assisted dying, which operates under entirely separate state legislation with its own eligibility process.
How do you make a valid advance care directive?
- Get the right form. Use your state or territory’s official statutory form if one exists. In NSW, where there’s no mandated form, use a clearly worded written document and consider having a lawyer check it.
- Reflect on your values first. Write down what matters to you (independence, avoiding prolonged ventilation, staying at home) before drafting specific instructions.
- Decide on instructional statements. Be concrete about treatments you’d refuse or accept in defined circumstances, rather than vague statements like “no heroic measures.”
- Appoint a substitute decision-maker if your jurisdiction allows it, naming someone who understands your wishes and is willing to advocate for them.
- Sign and witness it correctly. Follow your state’s witnessing rules exactly, since a defective signing can undermine the whole document.
- Distribute copies. Give copies to your GP, your substitute decision-maker, and close family, and consider uploading it to My Health Record so hospital staff can find it quickly.
Pro Tip: If you’re refusing a specific life sustaining treatment, ask your GP or specialist to write a short note confirming they discussed the decision with you while you had capacity. That single document often carries more weight in an emergency room than the directive alone.
Who should you appoint as your substitute decision-maker?
Every state uses a different title for this role: enduring guardian in NSW and South Australia, medical treatment decision maker in Victoria, and person responsible in various contexts where no formal appointment exists. Whatever the title, the legal duty is the same. A health professional must try to locate and generally follow a relevant, valid directive, and your substitute is expected to make decisions based on your directive first, then your known wishes, rather than what they personally think is best.
When choosing someone, ask:
- Will they actually follow your written wishes under pressure from other relatives?
- Do they live close enough, and are they willing to act quickly in a crisis?
- Have you discussed specific scenarios with them, not just the general idea?
Avoid appointing someone purely out of family obligation if they’ve expressed discomfort with your wishes. That mismatch is one of the most common sources of later disputes, and getting the appointment paperwork right matters just as much as the person you choose, as we’ve covered when reviewing enduring guardian forms in NSW.
Where should you store your directive, and how do you update it?
Keep copies with your GP, your substitute decision-maker, and immediate family, and store the original somewhere easy for others to find, not locked away where nobody knows to look. Uploading it to My Health Record means treating hospital staff can pull it up instantly during an emergency.
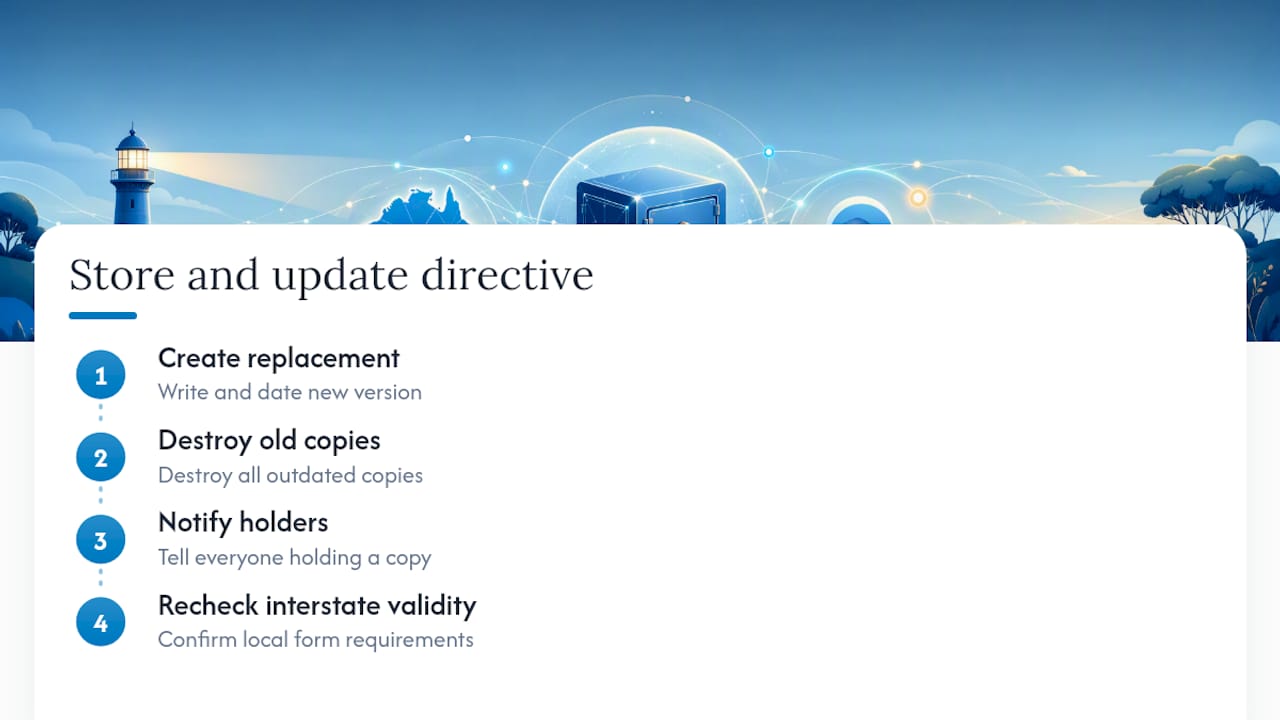
To update or revoke a directive, write and date a new version, destroy old copies, and tell everyone holding a copy that it’s been replaced. If you move interstate, recheck the local form requirements rather than assuming your existing directive is automatically valid there.
What legal problems most often derail an advance care directive?
Vague wording is the single biggest cause of disputes. “No heroic measures” means different things to different doctors; “no mechanical ventilation if I have no reasonable prospect of regaining consciousness” gives clinicians something concrete to act on.
- Vagueness: replace general statements with specific, scenario based instructions.
- Form errors: missing witness signatures or an undated document can undermine the whole thing, particularly in states with strict statutory requirements.
- Family disputes: disagreement often erupts when relatives weren’t told a directive existed or don’t understand why it says what it says.
New South Wales needs particular care here. Because it has no dedicated Act, courts and clinicians weigh common law factors like clarity and evidence of capacity more heavily than in states with a prescribed form. Attaching a short certification from your treating clinician confirming your capacity at the time, alongside a documented family conversation, substantially reduces the chance of a directive being challenged or ignored later.
Pro Tip: Don’t just tell your family you have a directive. Walk them through the actual instructions once, in plain language, so nobody is hearing them for the first time in a hospital corridor.
A lawyer’s view: when advance care directives need legal review
Most straightforward directives don’t need a lawyer. Where legal review earns its cost is in complex family situations, blended families, cross-jurisdiction moves, or where a directive might contradict another document, such as an enduring power of attorney or a Will. Lawyers reviewing directives typically check three things: whether there’s contemporaneous evidence of capacity, whether the wording clearly applies to the medical scenario that actually arose, and whether it conflicts with other appointments you’ve made.
Disputes over validity almost always come back to those same two questions: was it made voluntarily, with capacity, and does the wording actually cover what happened. Getting that right at the drafting stage, rather than arguing about it in a hospital, is the whole point of a proper review. Some law firms offer a complimentary 30 minute consultation to check exactly this before it becomes a problem.
— George
Funding Your Legal Matter — No Win, No Fee
Legal costs shouldn’t be the reason someone with a genuine estate or inheritance dispute walks away from a legitimate claim. Simons George Legal offers No Win, No Fee arrangements for eligible wills and estate disputes, including contested will matters and family provision claims. Eligibility isn’t assumed; it’s checked properly during your free initial consultation, where the firm reviews your situation and tells you honestly whether a conditional arrangement applies.
The point of this is simple: removing the upfront cost barrier so people with a real claim aren’t priced out of pursuing it. If you think you may have grounds for a dispute connected to a will, estate, or advance care directive conflict, book a free case assessment and find out where you actually stand.
No Win, No Fee arrangements are subject to case eligibility and a written costs agreement. Liability limited by a scheme approved under Professional Standards Legislation.
This article is general information, not a substitute for advice from a qualified lawyer. Consult a qualified legal professional about your own circumstances before acting on anything here.
Sources
- Advance care directives | End of Life Law (QUT)
- Advance care directive | Australian Government Department of Health
- Advance care directive | Public Advocate Victoria
- Advance care directive resources | NSW Health
FAQ
Can a doctor override an advance care directive?
A doctor can’t simply override a valid, relevant directive that clearly applies to the situation, since health professionals must try to locate and generally follow it. They can question its validity if there’s doubt about capacity at the time it was made, or if the wording doesn’t clearly cover the medical scenario in front of them.
Can someone with dementia make an advance care directive?
Yes, provided they still have decision-making capacity for that specific decision at the time of signing, since an ACD only takes effect once capacity is lost. Early-stage dementia doesn’t automatically remove capacity, but getting a clinician to document your understanding at the time strengthens the directive later.
What legal issues commonly arise with advance care directives, and how do you avoid them?
The three most common problems are vague wording, form or witnessing errors, and family disputes over what the person actually wanted. You reduce all three by using clear, scenario specific instructions, following your state’s witnessing rules exactly, and talking the directive through with family and clinicians before it’s ever needed.
Can you give an example of an advance care directive in practice?
A common example is someone stating they refuse mechanical ventilation if they have no reasonable prospect of regaining consciousness after a catastrophic brain injury, combined with appointing their spouse as substitute decision-maker. Another is a values statement prioritising comfort over life extension in a terminal illness, which guides a substitute even where no specific instruction covers the exact situation.
Is a living will the same as a power of attorney?
No. A living will (Advance Care Directive) covers health and medical decisions, while an enduring power of attorney covers financial and legal decisions. Many people need both, appointed separately, as part of a complete estate plan.